
Category: News

  • Curiosity: The Game Changer in Relationships

    Curiosity: The Game Changer in Relationships

    The Game Changer in Relationships: Curiosity Over Justification

    There is a moment in almost every relationship conflict when the conversation reaches a fork in the road. It may begin with a forgotten phone call, an impatient tone of voice, an unanswered text message or the familiar words:

    “You never listen to me.”

    In that moment, there are two very different paths available.

    One path leads towards justification. The other leads towards curiosity.

    The difference between them can determine whether two people move into conflict drift or create connection.

    Most of us don’t consciously choose justification. It simply arises as a default as our brains are wired for war. As we read the signs, the sound of the voice, the frown, the eye roll and walking away our primitive parts of our brain engage and we go to war. Before we have even realised what is happening we start to defend ourself

    “That’s not true.”

    “I do listen.”

    “You don’t understand how stressful my day was.”

    “What about all the times I’ve been there for you?”

    Suddenly, the conversation is no longer about understanding one another or taking care of the space in the middle, that couple bubble, that connection.

    It becomes a courtroom. Each person presents evidence. Each person defends their intentions. Each person quietly hopes the jury will declare them innocent.

    Yet relationships rarely heal because someone finally proves they were right. And if you are fighting about memory ie who said what when, they you are both right and both wrong!

    We heal when someone becomes curious enough to ask,

    “Tell me more.”

    Why We Justify

    Justification is rarely selfish or uncaring. Most often, it is psychobiological.

    When we perceive we are being criticised, misunderstood or blamed, our sympathetic nervous system (fight and flight system) automatically prepares us for danger. Long before we consciously choose our response, our body has already begun responding as though we are under threat.

    Our heart beats faster. Our breathing becomes shallow. Our muscles tighten. Stress hormones such as adrenaline and noradrenaline prepare us to defend ourselves. Then the cortisol clicks in! Our reptilian brains evolve over thousands of years, a response that helped our ancestors survive physical danger, engages!

    Today, however, the greatest threats are often emotional.

    • A threat to our identity.
    • A threat to our belonging.
    • A threat to feeling loved.
    • A threat to believing we are enough.

    So when a partner says,

    “I felt hurt when you didn’t call,”

    our nervous system may hear,

    “You’re failing me.”

    “You’re a terrible partner.”

    “You’re letting me down.”

    Without even realising it, we stop listening for understanding and begin listening for danger. The brain shifts from connection to protection.

    The emotional centres responsible for detecting threat become highly active, while the prefrontal cortex—the part of the brain responsible for empathy, curiosity, perspective-taking and thoughtful decision-making—becomes less available.

    We are no longer asking, “What is happening for my partner?”

    Instead, our nervous system asks, “How do I protect myself?”

    And so we justify.

    “I was busy.”

    “I told you I had meetings.”

    “You know how stressful work has been.”

    Everything we say may be true, but truth spoken from a defensive nervous system does not meet a need to be heard, understood, acknowledgement, for connection, for safety and care.

    When Two Nervous Systems Go to War

    The moment one person needs to be heard and isn’t, their nervous system becomes activated too.

    • They speak louder.
    • You defend yourself harder.
    • They become more emotional.
    • You become more certain.
    • They pursue.
    • You withdraw.

    Or perhaps both of you fight.

    The original issue quietly disappears beneath two nervous systems desperately trying to protect themselves as well as get their needs met!

    What looked like an argument about dishes, money or a phone call has become something much deeper.

    It has become two human beings asking silent questions.

    Do I matter?

    Am I safe with you?

    Do you understand me?

    Do I matter to you?

    Will you reject me?

    Will you choose me?

    Genuine intimacy requires enough safety for people to remain present with themselves and with one another, even when difficult emotions arise. When the nervous system becomes overwhelmed, curiosity naturally narrows and self-protection takes over.

    This is why telling your partner to “calm down” rarely works! Yet shifting gears to hear the need that is trying to be met does.

    An activated nervous system cannot simply be reasoned into feeling safe. Sometimes healing begins by slowing everything down.

    • Breathing.
    • Softening our voice
    • Sitting down and facing each other
    • Waving the flag of friendliness before you go offline
    • Taking a break and coming back when regulated to discuss the issues

    The Hidden Longing Beneath Every Argument

    One of the greatest shifts whether we are a couple, a parent, a daughter, sibling, colleague or employer, we can make is learning to hear what sits beneath the words. Listening for feelings and needs trying to be met.

    When someone says,

    “You never help me,”

    perhaps what they are really saying is, “I feel lonely and need support”

    “You don’t care about me.”

    may actually mean, “I want to matter to you”

    “You’re always on your phone.”

    may really be saying, “I miss connecting with you”

    Justification responds to the accusation.

    Curiosity listens for the longing, the feelings and needs.

    This is why curiosity is so powerful as it maintains connection whilst taking care of the space in the middle and not default to pro-self.

    Rather than asking, “How do I prove I’m right?” it quietly wonders,

    “What pain am I hearing underneath these words? What need is trying to be met?”

    Shifting Gears: From Defending to Listening

    Curiosity is more than asking good questions. It is learning to shift gears.

    When we become defensive, we naturally listen for mistakes in our partner’s story. We prepare our response before they have even finished speaking.

    • We interrupt.
    • We explain.
    • We defend.

    Curiosity asks us to able to hold the tension enough to temporarily put our own story aside, for a moment, and become deeply interested in the others.

    This is where active and empathetic listening become transformational.

    Active listening means being present and feeding back the feelings and facts that are trying to be expressed.

    Empathetic listening goes even deeper.

    It listens for feelings and unmet needs embedded in the longing beneath the behaviour and words.

    Instead of responding with defensiveness when you hear:

    “You never listen,”

    we begin by responding by saying

    “It sounds like you are eager to be heard around this?”

    Or

    “Is it that you are anxious as you would really like to connect?”

    Notice that none of these statements require agreement and there is no “I” as you have left the message with the other.

    It is simply communicating to gain understanding first.

    It is only after we have gained understanding of the other and we are on the right track not consumed by assumptions, do we gently offer our own experience in the form of feelings and needs.

    “Thank you for sharing that. Would you be willing to hear my experience about the situation?”

    This is one of the beautiful paradoxes of relationships.

    The fastest way to be understood is often to help the other person feel understood first.

    Your feelings matter equally. But two activated nervous systems cannot truly listen at the same time. Someone has to shift gears first.

    Curiosity Is Not Surrender

    Many people worry that curiosity means admitting they were wrong.

    It doesn’t.

    Curiosity is not agreement.

    It is not accepting blame for something you didn’t do.

    It is not tolerating abuse.

    Curiosity simply says,

    “Your experience matters enough for me to understand it before asking you to understand mine.”

    There is enormous strength in that. Because when people feel emotionally safe, they naturally become more curious about us in return.

    From Winning to Repair

    Healthy relationships are not built because we avoid conflict. They are built because we learn to repair after conflict., and quickly.

    Repair begins when we recognise that intention and impact are often different. You may never have intended to hurt someone. Yet they may still have experienced hurt.

    One simple sentence can change the entire direction of a conversation.

    “It looks like that really upset you?”

    That is not admitting malicious intent. It is acknowledging another person’s reality. And sometimes that is all the nervous system needs to begin relaxing.

    Protecting the Relationship Instead of Protecting Yourself

    The next time conflict begins, notice the moment you feel the urge to defend yourself.

    Pause. Get curious!

    Take one slow breath.

    Notice your body.

    Then ask yourself one question.

    “Am I trying to protect my position, or am I trying to protect this relationship?”

    Transformation does not emerge through pressure or persuasion, it emerges with tiny habits and grows from presence and emotional safety. It grows when curiosity becomes stronger than justification.

    Because perhaps the greatest act of love is not having the perfect answer. It is having the courage to remain curious.

    To listen before explaining.

    To understand before correcting.

    To reflect before reacting.

    To protect the relationship before protecting your ego.

    So before saying,

    “But…”

    pause. Ask,

    “Help me understand what is going on for you.”

    Listen for the feelings.

    Listen for the needs.

    Listen for the longing beneath the words and behaviour.

    Then, once the other knows they have been heard, gently share your own heart.

    Because love is rarely strengthened by proving who was right. It is strengthened when two people feel safe enough to stop defending themselves and begin discovering one another again.

    That is the quiet power of curiosity.

    And sometimes, it is the doorway that leads two people home to each other, to security, mutuality and respect.

  • Addiction, Dependence and Hyperbolic Tapering

    Addiction, Dependence and Hyperbolic Tapering

    by Julie Santall

    Judy’s Story

    Judy walked into my room clinging tightly to the arm of her partner. A tall, elegant woman of 69, she appeared frightened, vague and uncertain. She sat down without letting go of him. I noticed immediately her dependence on him and his apparent impatience with that dependence. Each time he shifted away, she reached for him again. Judy had brought him for support, but it quickly became clear that his presence was not helping her feel safe.

    Judy had been referred to me by a local wellness clinic. More than ten years earlier, she had been prescribed Cymbalta (duloxetine), a serotonin-norepinephrine reuptake inhibitor (SNRI), by her psychiatrist.

    SNRIs are based on the “monoamine hypothesis” of depression. They work by blocking the serotonin transporter (SERT) and norepinephrine transporter (NET), theoretically increasing signalling in parts of the brain involved in mood, attention and pain regulation. However, despite decades of use, the precise mechanisms of antidepressants and antipsychotics remain poorly understood.

    Judy had originally been prescribed 30 mg of Cymbalta. Several years earlier she had attempted to discontinue the medication and had successfully reduced to 5 mg. However, she dropped from 5 mg to zero too quickly and experienced severe withdrawal symptoms. Feeling “awful,” she returned to her doctor, who reinstated Cymbalta at 60 mg before later reducing it to 30 mg and adding Lexapro (escitalopram), an SSRI, to “assist” the withdrawal process.

    Her pharmacist raised concerns about serotonin syndrome, which caused Judy considerable anxiety. Serotonin syndrome is a potentially serious reaction caused by excessive serotonin activity, usually when multiple serotonergic medications are combined. Ironically, while stopping psychiatric medication too abruptly can be dangerous, adding medications can also create complications.

    This uncertainty led Judy to compulsively research her symptoms online using ChatGPT and other sources, which only intensified her fear.

    What Judy was actually experiencing was a combination of rapid withdrawal from psychotropic medication, multiple interacting prescriptions, escalating anxiety, poor sleep and eventually akathisia.

    Akathisia is a movement disorder characterised by an intense inner restlessness and an overwhelming urge to move. Although not life-threatening, it can be profoundly distressing and may contribute to agitation, despair and suicidal thinking.


    Neuroadaptation and Withdrawal

    Over the years Judy’s brain had adapted to the medications she was taking. This process, known as neuroadaptation, involves changes in receptor sensitivity and neurotransmitter regulation. When medications are withdrawn too quickly, the nervous system can become destabilised.

    Judy had experienced this before. In her twenties, after treatment for anorexia, she had abruptly stopped antidepressants and experienced withdrawal symptoms. Years later, when she attempted to stop Cymbalta rapidly under medical guidance, she again experienced severe withdrawal.

    Unfortunately, as often happens, her psychiatrist interpreted the withdrawal symptoms as a relapse of depression or anxiety and reinstated the medication at a higher dose.

    Withdrawal vs Relapse

    Distinguishing withdrawal from relapse is critical.

    Withdrawal symptoms typically begin within days of reducing or stopping medication. They may include:

    • dizziness
    • nausea
    • insomnia
    • “brain zaps” or electric shock sensations
    • anxiety and agitation
    • akathisia
    • intrusive or violent thoughts

    Withdrawal symptoms often improve if the medication is reinstated to the last stable dose.

    Relapse, on the other hand, usually develops gradually over weeks or months and mirrors the original emotional presentation prior to medication. It does not reliably improve with rapid dose increases.

    Repeated cycles of withdrawal and reinstatement can also contribute to what is known as kindling.

    Kindling

    Kindling refers to a phenomenon in which repeated cycles of substance use and withdrawal sensitise the nervous system, causing each withdrawal episode to become more severe.

    Historically associated with alcohol and benzodiazepines, kindling is now increasingly recognised in psychotropic drug withdrawal. Over time the nervous system becomes more reactive, increasing sensitivity to future reductions and making withdrawal progressively harder to tolerate.


    Polypharmacy and Nervous System Overload

    By the time Judy came to see me, she was experiencing severe anxiety, cognitive impairment and insomnia.

    Her psychiatrist had prescribed propranolol, a beta blocker often used to reduce physical symptoms of anxiety. When Judy reported ongoing insomnia, she was then prescribed olanzapine, an antipsychotic medication commonly used for sedation at low doses.

    The olanzapine caused significant morning sedation, so dexamphetamine was added to counteract the grogginess.

    At this point, multiple medications with opposing effects were interacting in her system simultaneously:

    • Cymbalta
    • Lexapro
    • propranolol
    • olanzapine
    • dexamphetamine

    The result was increasing agitation, anxiety and nervous system dysregulation.

    If I were to fully explain the pharmacological interactions between these drugs, it would require another article entirely. Suffice to say, it was clear why Judy’s nervous system was in such distress.


    Judy’s History

    Judy explained that in 2008 she had been working as a social worker in an adolescent mental health unit while raising four adopted children on her own, one of whom was autistic and required intensive care.

    She had never married. Work became a way of escaping the overwhelming responsibilities at home.

    She also described a childhood in which she had acted as her mother’s confidant and emotional support. Between the ages of 16 and her early twenties she had struggled with anorexia and had previously been prescribed antidepressants.

    To manage the overwhelm in adulthood, Judy increasingly relied on red wine. Eventually she entered a detox program, where she met the psychiatrist who first prescribed Cymbalta.

    Even before our work together began, Judy had already experienced one failed taper. Following standard pharmaceutical guidelines suggesting that withdrawal effects are mild and self-limiting, her psychiatrist reduced her rapidly from 60 mg to 30 mg.

    This history was significant because it suggested a sensitised or “kindled” nervous system. I knew she would likely require a very gradual taper to minimise further harm.


    Dependence vs Addiction

    The terms dependence and addiction are often used interchangeably, but they describe different phenomena.

    Dependence

    Dependence is primarily physiological. The body adapts to the presence of a substance and begins to rely on it to function normally.

    Characteristics of dependence include:

    • tolerance
    • withdrawal symptoms when stopping
    • neuroadaptation within the nervous system

    A person can be dependent without being addicted. For example, someone prescribed opioid medication for severe pain may develop physical dependence without compulsive misuse.

    Addiction

    Addiction is behavioural and psychological. It involves compulsive use despite harmful consequences.

    Characteristics of addiction include:

    • loss of control
    • compulsive cravings
    • continued use despite harm
    • psychological reliance to manage emotional pain

    From an Internal Family Systems (IFS) perspective, addictive behaviours can be understood as protective “firefighter” parts attempting to numb distress or emotional overwhelm.

    In Judy’s case, her primary issue was dependence rather than addiction. Her brain had adapted to long-term exposure to psychotropic medication.


    The Brain’s Adaptation to Medication

    With antidepressants and antipsychotics, the brain adapts to the constant presence of the drug.

    The widely promoted “chemical imbalance” theory of depression has been increasingly challenged in recent years. Critics argue that the theory was oversimplified and heavily marketed by pharmaceutical companies.

    The brain continually strives for homeostasis. In response to ongoing medication exposure, receptor sensitivity changes and neurotransmitter systems recalibrate.

    Over time the nervous system becomes dependent on the presence of the medication.

    This is why reducing psychiatric medication can become so difficult.


    Hyperbolic Tapering

    Judy wanted to discontinue her medication safely. Given her history, I believed she would need to taper hyperbolically.

    Hyperbolic tapering involves making progressively smaller reductions as the dose becomes lower.

    Rather than reducing linearly — for example by dropping 10 mg each time — reductions become increasingly gradual near the end of the taper.

    For example:

    • 40 mg → 20 mg
    • 20 mg → 10 mg
    • 10 mg → 5 mg
    • 5 mg → 2.5 mg

    Another common approach is reducing by approximately 10% of the previous dose and holding for periods of stabilisation between reductions.

    Why Hyperbolic Tapering Matters

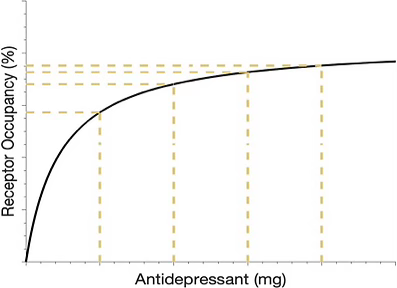
    Research using receptor occupancy studies suggests that even low doses of antidepressants can occupy a very high percentage of brain receptors.

    This means that small reductions at lower doses may have disproportionately large effects on the nervous system.

    In practice, this is why dropping from 5 mg to zero can feel far more destabilising than reducing from 40 mg to 35 mg.

    Psychiatrists and researchers such as Mark Horowitz and David Taylor discuss this extensively in The Maudsley Deprescribing Guidelines (2024). Anders Sørensen also explores these principles in Crossing Zero (2025).


    The Emotional Dimension

    Judy had spent much of her life moving away from painful emotions through work, wine and eventually medication.

    This is profoundly human. Most of us seek relief from emotional pain.

    However, tapering medication often means that long-suppressed emotions begin to surface again.

    The therapeutic task is not simply medication reduction. It is helping the client build the capacity to tolerate and understand difficult emotional and bodily experiences.

    Antidepressants can dampen emotional intensity, but they do not resolve the underlying life experiences, attachment wounds or unresolved trauma contributing to suffering.

    Judy had never truly stopped to examine:

    • why she adopted four children while still very young and living at home
    • why she developed anorexia at sixteen
    • why she relied so heavily on work and caretaking
    • why she felt unable to tolerate stillness or emotional discomfort

    Eventually, her attempts to numb overwhelm resulted in dependence on a complex medication regimen that caused significant iatrogenic harm.


    A Kindled Nervous System

    Judy’s tapering journey has been difficult.

    Despite collaborative planning with her integrative doctor and myself, she struggled to follow the tapering schedule consistently. Feeling temporarily stable after an initial reduction, she reduced again too quickly.

    Her nervous system reacted intensely.

    Once a nervous system becomes highly sensitised or kindled, even minor changes — including supplements or seemingly benign medications — can trigger significant symptoms.

    At that point, there is often no medication that can simply “fix” the problem. The work becomes learning how to gradually tolerate and regulate bodily sensations rather than constantly escaping them.

    Judy also developed cognitive difficulties after multiple medication changes and additions.

    Compounding matters further, her partner responded with frustration and criticism rather than emotional safety. From an attachment perspective, this lack of safety likely amplified her nervous system distress.

    When overwhelmed, Judy repeatedly sought reassurance from her psychiatrist, whose primary response was further medication changes.

    As the saying goes: when your only tool is a hammer, every problem begins to look like a nail.


    The Role of Counselling

    My primary focus with clients withdrawing from substances or psychotropic medications is resourcing.

    In practical terms, this means helping them find even brief moments of safety, steadiness or calm within the body and mind.

    Only when the nervous system has some degree of stability can deeper therapeutic work occur.

    The goal is not merely to remove medication, but to help clients understand themselves more deeply rather than relying solely on substances or compulsive behaviours to manage distress.

    Judy’s story is ongoing.

    I hold hope for her because I have seen many people successfully taper from psychiatric medication when the process is gradual, collaborative and carefully supported.

    I am one of them.

    Her story highlights both the potential dangers of rapid psychotropic withdrawal and the importance of compassionate, informed care.

    While her experience is extreme, it is not hopeless.

    Every tapering journey is individual. With appropriate pacing, support and nervous system regulation, many people can successfully reduce or discontinue psychiatric medication.


    References

    Horowitz, M., & Taylor, D. (2024). The Maudsley Deprescribing Guidelines. Wiley Blackwell.

    O’Brien, C. P., Volkow, N., & Li, T.-K. (2006). What’s in a word? Addiction versus dependence in DSM-V. American Journal of Psychiatry, 163(5), 764–765.

    Sørensen, A. (2025). Crossing Zero. North and Vale.

    In his book ‘Crossing Zero’ (2025), Anders Sorenson explains the receptor occupancy/dose relationship. For example, at only 20mg of Prozac – 86% of the brain’s receptors are occupied with serotonin from the drug. This means that the smaller the dose the greater the impact it has on the brain. Mark Horowitz and David Taylor also describe this in their comprehensive book ‘The Maudsley Deprescribing Guidelines’ (2024)

    Whitaker, R. (2010). Anatomy of an Epidemic. Crown Publishing Group.

    In his book “Anatomy of an Epidemic” (2010) Robert Whitaker summarises a World Health Organisation study (1998) showing that people diagnosed and treated with psychiatric medication for depression had worse outcomes than those not exposed to drugs. 

    Mark Horowitz interview on withdrawal, relapse and hyperbolic tapering:

    In this interview Mark Horowitz discusses the difference between withdrawal and relapse, the effects of long-term antidepressant use and the role of clinicians and peer support in de prescribing and hyperbolic tapering. 

    Further Reading

    Farmer, Adele ‘What I have learnt from helping thousands of people taper off antidepressants and other psychotropic medications’ https://pmc.ncbi.nlm.nih.gov/articles/PMC7970174

  • What is Held In and What is Held Out?

    What is Held In and What is Held Out?

    Many years ago, whilst immersed in a silent retreat, in the bathroom of all places, I asked a question as my partner at the time walked past. The answer resulted in everything disappearing, and I experienced that we are consciousness itself. I saw how lifetimes don’t exist, there is no time and no space it is simply all now, I saw how we are never born and never die — only the body does. I have never been the same since.

    The question was: How can I experience nothing when my enlightened teacher walks past, and nothing when my partner walks past?

    My whole being replied, “Because you are nothing.”

    I laughed so deeply and with pure joy that everything disappeared.

    As a therapist, and for many gurus, how do you invite someone — including yourself when the ego takes over again — to that place of consciousness itself? Simple, sublime; there is nothing and everything at the same time. We can point to it, yet the moment the mind tries to grasp it, we are back in the mind.

    How do we navigate feelings, thoughts, and pain bodies enough to quieten them so we can experience what never leaves us, what the mind continually overlooks in its searching?

    I have discovered a technique that honours the premise that we are simply energy vibrating at a certain frequency. Scientists understand this in terms of viruses. Each virus vibrates at a certain frequency. Thoughts vibrate at a certain frequency, and we can observe their effect on water. Feelings vibrate at a certain frequency, and we experience their effects within our bodies.

    They are like radio waves moving through us, but sometimes they get stuck and we begin vibrating at that frequency. This can be distressing because it is not the vibration of who we truly are. We call this suffering.

    This is what we hold in.

    Which also raises the question:

    What do you hold out?

    What delicious feelings, experiences, and sensations do you hold out?

    If radio waves come and go, then the good stuff moves through you too.

    Joel Young created a very quick technique called ‘Non-personal awareness’ that the mind will likely dismiss because of its simplicity. Yet it is a powerful process that meets the frequency of the thought, feeling, or pain body and disengages it from our being — in other words, sending it back where it came from, letting it move through you easefully.

    Want to know how?

    It is simple.

    It involves six sentences.

    Yep. Simple and elegant.

    Here’s how

    1. Firstly, grab a pen and paper, or journal or your phone so you can record your own dialogue.
    2. Secondly, think of something that challenges you, constricts you, that you hold in. Just vomit it onto the page, or by speaking into your phone on record, and see what words, feelings, behaviours, thoughts, sounds, movements appear that are paramount, repeated. What is the fundamental thing. It does not have to make sense. You do not have to analyse it or figure it out, it is just energy stuck.
    3. Take one of these which may have sounds and movements with it , without analysing it or trying to understand it or find parallels with your childhood, no interpretation needed, simply bring it into these sentences. For example, I may have deep feeling that people don’t care about me and a hand movement, and a sigh that goes with it.
      • Simply say (whilst adding the sigh and hand movement)
        • This people don’t care about me
        • This energy people don’t care about me
        • This pure energy people don’t care about me’
        • ‘This pure energy people don’t care about me is not personal’ (3 times)
        • This pure energy people don’t care about me is not personal’
        • This pure energy people don’t care about me is not personal’
        • This pure energy people don’t care about me is not personal and I am willing to experience it’
    4. Allow space for the sensations to arise, you can go as slow as you like. You may say the last sentence again.
    5. Wait until you feel the clarity appear again and maybe a natural aliveness arises.
    6. Now if energy is held in and it flows out, what is held out? What energy would you like to replace the energy that was held in that has now gone with? Maybe joy, ease, love, peace…find yours. Sometimes it arises naturally after the first part of the exercise. For example: ‘Connection’ arose after the first part of the exercise.
    7. Take this feeling, sensation, whatever it is and bring it into the same sentences:
      • Simply say (adding your feeling in)
        • ‘This connection’
        • ‘This energy of connection’
        • ‘This pure energy of connection’
        • ‘This pure energy of connection is not personal’ (3 times)
        • This pure energy of connection is not personal and I am willing to experience it’

    Simply notice what happens.

    There is no need for analysing, interpretation, or fixing.

    Simply experience the energy moving through you.

    Some people have trauma leave their body, which can be overwhelming, I would simply allow the body to shake, cry and not to fear the movement of the energy. Simply repeat the sentences slowly.

    30 Day Challenge

    In this time in history, we are continually bombarded by radio waves — information, thoughts, pain bodies, feelings, and countless electronic frequencies that can interfere with our connection to our own true vibrational frequency.

    Perhaps this is an opportunity.

    An opportunity to allow these energies to move out and to let who you truly are move in.

    So here is the challenge.

    For 30 days, use your phone, journal, or a piece of paper and spend just a few minutes each day with this process.

    Notice what you are holding in.

    Everyday bring something that you hold in to the challenge by using the non-personal awareness exercise. Remember to invite yourself to experience what you hold out too after you have completed the first round, or a few rounds of what energy you hold in.

    You may discover that the thoughts, feelings, stories, and sensations that once seemed so personal are simply energy moving through awareness.

    Perhaps beneath the noise, beneath the stories, beneath the endless radio waves moving through the mind and body, there is a natural clarity, aliveness, peace, love, connection, or joy waiting to be experienced.

    Not because you created it.

    Not because you earned it.

    But because it is already here.

    The challenge is simple.

    Thirty days.

    A few minutes a day.

    Six sentences.

    And a willingness to experience what arises.

    See what happens.

    Let’s share the energy and add your comments below